Pregnancy week 32: practice breathing, real bag-packing

Inside, breathing drills run in rhythmic sets — the first cry is in training. Outside, this is the week the hospital bag stops being a list and becomes a bag by the door.
The bag by the door
Thirty-two weeks is the packing deadline for a reason: from here, 'early' is no longer rare enough to ignore. Most babies wait for term — but the house that's ready doesn't have to bet on it.
So this week the bag gets finished — not listed, packed. Papers pouch in, clothes in, baby kit in, the taped top-up list (charger, glasses, snacks) on the outside. By the door, known to all.
Inside, the baby is doing its own readiness drills — practice breathing now runs in rhythmic sets, the swallow-digest loop is polished, and the skeleton hardens daily against your calcium account.
Your baby this week
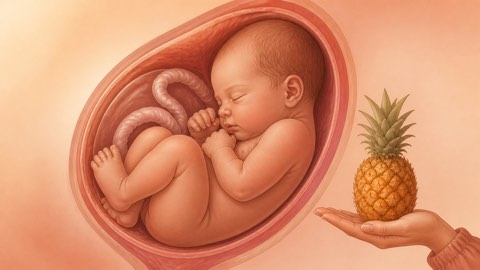
The baby is about forty-two centimetres and seventeen to eighteen hundred grams — and from this week, gains speed up again: two hundred to two hundred fifty grams a week.
The skin is losing its wrinkles as fat fills in; the lanugo keeps shedding; toenails are complete. What remains is mostly weight, lung-finishing, and immune stocking.
Most babies are head-down by now, settling deeper. Movements are strong but cramped — rolls, stretches and jabs rather than flips. Same pattern rule: the count is the count.
Read next

Changes in your body
Braxton Hicks are more frequent and more convincing now — some take a breath away. The distinguishers hold: irregular, easing with rest and water, not building. You'll re-run this test many times; that's normal life at thirty-two weeks.
Pelvic and pubic-bone aches may sharpen — the joints are loosening on schedule. The waddle widens; turning in bed is a logged manoeuvre. A pillow between the knees and 'knees together' when turning both help.
Fatigue is back to first-trimester levels — carrying this much construction is a full-time job. The afternoon lie-down is medicine now, not indulgence.
What to do this week
Pack the bag completely this week — mother's side, baby's side, papers pouch, escort's basics. Taped list on top for the last-minute items. Done means done: zipped, by the door.
Confirm the week-34 visit and any repeat scan the doctor wants. The two-weekly rhythm has two visits left before weekly begins.
Have the 'what if it starts early' conversation with the household — waters breaking or rhythmic pains before thirty-seven means hospital immediately with the bag; 108 if no car; nobody waits for morning.
If cord-blood banking or any birth-day decisions (who's allowed in, photography, the first-hour skin-to-skin request) matter to you, decide and write them on the fridge sheet now — the labour room is a bad negotiation venue.
Week 32 at a glance
The week's essentials in one place. Your doctor may adjust these for your situation.
| Item | In week 32 |
|---|---|
| Main event | Rhythmic breathing drills; hardening skeleton |
| Baby's size | ~42 cm, 1.7-1.8 kg — gaining 200+ g/week |
| Deadline | Hospital bag packed and by the door |
| Possible symptoms | Stronger Braxton Hicks, pelvic aches, deep fatigue |
| Household drill | Early-start plan spoken aloud, 108 known |
| Decisions | Birth-day preferences on the fridge sheet |
| Visits | Two more two-weeklies, then weekly |
When to see a doctor at once
The standing list — movement slump, bleeding, rhythmic tightening, watery discharge, the triad, fever, urinary burning, calf swelling, night itch: same-day.
The waters question, answered before it's asked: a gush is unmistakable, but a slow trickle that keeps wetting a pad is the same event in disguise. Either one, at any hour, is hospital-now — amniotic fluid has no wait-and-see setting.
This article is general information only and no substitute for personal medical advice. The person who can advise you knowing your health, your medicines and your previous pregnancies is your obstetrician, or the doctor at your nearest health centre.
Work out your due date
Enter the first day of your last period and your cycle length — your estimated due date, this week's count and the anomaly scan window all appear right here.
It is only an estimate — most babies aren't born on the exact date. A first-trimester scan dates a pregnancy more accurately; in the end, your doctor's date is the one that counts.
Frequently asked questions
My Braxton Hicks are strong enough to stop me mid-task
still 'practice'? — Strength alone doesn't reclassify them; rhythm and progression do. Strong-but-random, easing with rest: practice. Any strength arriving on a schedule that holds or tightens: the real kind — call.
What if the baby is still not head-down?
At thirty-two, roughly one in ten aren't, and most of those turn by thirty-six on their own. The decision tree (positions, ECV — the turning procedure, or a planned caesarean) only starts at thirty-six. This week it's a note, not a problem.
How big should the bag actually be?
One medium bag for you, one small for the baby, and discipline. Hospitals supply more than people expect; homes are usually twenty minutes away. Bag bloat is real and the person carrying it mid-labour is not you.
I'm suddenly scared of the delivery itself
is that normal this late? — It's normal precisely because it's this late — the abstract is becoming concrete. Two treatments work: information (the antenatal class's labour module, your doctor walking you through the stages) and company (naming the fear aloud to someone who's done it). Fear shrinks when it's specific.
Sources
Every clinical figure on this page is taken from the guidelines below. Where our numbers and your doctor's differ, ask which guideline they follow.
- WHO. WHO recommendations on antenatal care for a positive pregnancy experience (2016)Supports the page's framework of scheduled antenatal visits at regular intervals (two-weekly rhythm moving to weekly) and the advice to seek immediate care for warning signs such as bleeding, ruptured membranes, fever, and rhythmic contractions before 37 weeks.
- NICE. Antenatal care (NG201) (2021)Supports the description of Braxton Hicks contractions and their distinguishing features (irregular, relieved by rest), the advice to attend hospital immediately for suspected rupture of membranes (gush or persistent trickle), and the recommendation for regular fetal movement monitoring using a consistent pattern rather than a fixed count.
- RCOG. Rupture of Membranes Before Labour at Term (Patient Information Leaflet) (2023)Supports the page's explanation that both a sudden gush and a slow continuous trickle wetting a pad represent rupture of membranes requiring immediate hospital assessment with no wait-and-see approach.
- WHO. Preterm birth (Fact sheet) (2023)Supports the page's statement that labour and rupture of membranes occurring before 37 weeks of gestation constitutes preterm birth requiring urgent clinical management.
Reviewed by
- Nakul Phatak — CEO, theAsianparent India & IndonesiaHead of theAsianparent India; father of one
- Roshni Chugani — Head of Marketing, theAsianparent India & Singapore12 years in the mother-and-baby space; mother of two
Published by: theAsianparent editorial team