Pregnancy week 38: full polish, full alert

Everything is built; the factory is doing quality passes — brain wiring by the billion, fat by the day. Your work is monitoring, patience, and keeping the drill warm.
Quality-control days
Thirty-eight weeks is quality control: the organs are built and running; what's happening now is refinement — the brain adding connections at a rate it will never match again, the lungs stockpiling more surfactant, the body layering the fat that will manage the world's first cold air.
These are the days that test patience most — everything is ready, nothing is happening, and the phone's aunty-network asks daily. The honest frame: the baby is choosing its birthday from a very short list, and every day it waits is a small deposit in its account.
The clinical frame is equally simple: at thirty-eight, monitoring is the job — the weekly visit, the daily count, the BP watch. Boring is the target state. Boring means all systems normal.
Your baby this week
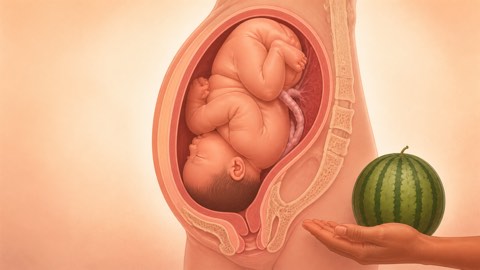
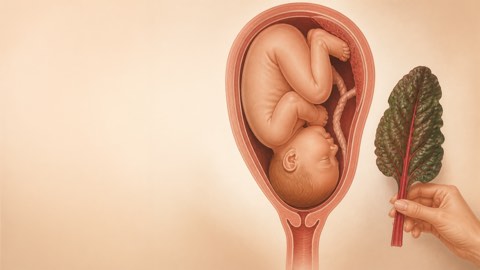
The baby is about forty-nine and a half centimetres, three kilos or a little more, gaining daily. The lanugo is gone; vernix remains in the creases for delivery day.
The first stool (meconium) is loaded and waiting for its famous first nappy. The eyes are their birth colour for now — the final shade settles across infancy.
The baby has a firm grip, working reflexes (root, suck, startle) and a known voice list. It is, in every testable way, a newborn who happens to still be inside.
Read next

Changes in your body
Contractions of every rank rehearse daily now. You are, by this point, the local expert in classifying them — trust the classification, and phone when a pattern holds.
Swelling is at its peak legality: soft, both-ankle, evening swelling is standard issue. The face-fingers-sudden kind keeps its same-day BP rule to the last day.
The body may 'empty the decks' before labour — loose motions and a burst of energy sometimes precede it by a day or two. Neither is proof of anything; both earn a note and a normal dinner.
What to do this week
Attend the weekly check; ask each time: BP fine, fluid fine, position unchanged, anything about the post-date plan updated?
Keep the count's fixed slot through the excitement — the daily ten remains the single most useful thing you personally monitor.
Keep the escorts warm: one message a week — 'still on, phone loud at night?' The drill is a muscle; a weekly twitch keeps it alive.
Sleep-bank shamelessly: naps, early nights, late mornings if life allows. Labour is an athletic event of unknown start time; rest is the only training left on the plan.
Week 38 at a glance
The week's essentials in one place. Your doctor may adjust these for your situation.
| Item | In week 38 |
|---|---|
| Main event | Quality-control days — brain, fat, surfactant |
| Baby's size | ~49.5 cm, 3+ kg |
| Status | A newborn who happens to be inside |
| Possible signs | Deck-clearing, energy bursts, expert-level rehearsals |
| Target state | Boring — it means all systems normal |
| Keep warm | The count, the visits, the escorts, the sleep bank |
| The frame | Every waiting day is a deposit |
When to see a doctor at once
The two lists run unchanged and un-negotiable: go-now (waters, bright-red bleeding, five-minute pains, headache-plus-vision, failed count) and call-first (rhythmic tens, slow counts, fever, burning, unease). The count keeps its full authority to the last morning — term babies slump for real reasons too.
One note for the eager: routine 'let's just induce, everyone's ready' requests before there's a medical reason trade real benefit for real risk. Induction has proper indications — the post-date plan, BP, fluid, growth — and your doctor will use them when they arrive. Impatience isn't one of them.
This article is general information only and no substitute for personal medical advice. The person who can advise you knowing your health, your medicines and your previous pregnancies is your obstetrician, or the doctor at your nearest health centre.
Work out your due date
Enter the first day of your last period and your cycle length — your estimated due date, this week's count and the anomaly scan window all appear right here.
It is only an estimate — most babies aren't born on the exact date. A first-trimester scan dates a pregnancy more accurately; in the end, your doctor's date is the one that counts.
Frequently asked questions
The internet says walking, dates, spicy food, and… intimacy… near term
allowed? — All allowed in a normal pregnancy at term (intimacy included, unless your doctor has said otherwise for placenta or waters reasons) — and none of them reliably start labour. They're comfort, not levers. The baby has the only calendar.
My mother delivered both of us 'early'
does that run in families? — Timing patterns have some family tendency, but it's weak prediction — every pregnancy keeps its own counsel. Interesting note for tea; useless for planning. The bag by the door is the only planning that works.
How long does labour actually take
the stories terrify me? — First labours average twelve to eighteen hours from organised contractions, most of it the slow early phase best spent at home breathing and walking (per your doctor's timing instructions). The screaming-dash of the movies is the last hour, dramatised. The antenatal class's stage map is the antidote to the stories.
What if my waters break in the market/bus/at a function?
Then a story gets born along with the baby. Practically: pad or cloth, phone the hospital, go — wet clothes and all; labour wards have seen everything and judge nothing. The only wrong move is going home to shower and wait. Water = go, from anywhere.
Sources
Every clinical figure on this page is taken from the guidelines below. Where our numbers and your doctor's differ, ask which guideline they follow.
- WHO. WHO recommendations on antenatal care for a positive pregnancy experience (2016)Supports the page's emphasis on regular antenatal monitoring at 38 weeks including blood pressure surveillance and the clinical importance of detecting signs such as facial/finger swelling with sudden BP rise as a same-day concern.
- NICE. Antenatal care (NG201) (2021)Supports the recommendation for weekly antenatal visits in late pregnancy, monitoring of BP and amniotic fluid, the clinical significance of sudden facial/finger oedema with hypertension, and the position that elective induction requires proper clinical indications rather than patient impatience.
- RCOG. Reduced Fetal Movements (Green-top Guideline No. 57) (2011)Supports the page's consistent emphasis on the daily fetal movement count (ten movements) as a monitoring tool through to term, and its inclusion of a failed or slow count as a 'go now' or 'call first' emergency trigger.
- ACOG. ACOG Practice Bulletin No. 107: Induction of Labor (2009)Supports the page's statement that elective induction before a medical indication exists (such as post-dates, BP abnormality, fluid or growth concerns) trades real benefit for real risk, and that impatience is not a clinical indication for induction.
- MoHFW. Pradhan Mantri Surakshit Matritva Abhiyan — Antenatal Care Guidelines (2016)Supports the page's advice to attend the weekly late-pregnancy check and to ask about BP, fluid level, fetal position, and the post-date management plan — consistent with India's national ANC protocols.
- NICE. Hypertension in pregnancy: diagnosis and management (NG133) (2019)Supports the page's same-day BP rule for sudden facial and finger swelling, and its inclusion of headache with visual disturbance as a 'go now' emergency symptom at 38 weeks.
Reviewed by
- Nakul Phatak — CEO, theAsianparent India & IndonesiaHead of theAsianparent India; father of one
- Roshni Chugani — Head of Marketing, theAsianparent India & Singapore12 years in the mother-and-baby space; mother of two
Published by: theAsianparent editorial team